
In short
Ankle arthritis is wear of the cartilage in the ankle joint, so the bones rub together and cause pain, stiffness, swelling and reduced movement. Unlike the hip or knee, it most often follows an injury such as a fracture or repeated sprains. Supportive or rocker-soled shoes, insoles, physiotherapy and injections help in the earlier stages. For advanced arthritis, ankle fusion and ankle replacement both give excellent pain relief, and the right choice depends on your age, activity, bone quality and alignment.
What is ankle arthritis?
The ankle joint is covered in smooth cartilage that lets the bones glide. In arthritis this cartilage wears away, so the bones rub together. This causes pain, stiffness, swelling and reduced movement, and can make walking, stairs or standing for long periods difficult. Unlike the hip or knee, where wear-and-tear arthritis is most common, ankle arthritis usually develops after an injury.
What causes it?
- Post-traumatic arthritis. The most common cause, after a broken ankle, dislocation or repeated sprains.
- Osteoarthritis. Age-related wear, less common in the ankle than other joints.
- Inflammatory arthritis, such as rheumatoid or psoriatic arthritis.
- Avascular necrosis. Poor blood supply to the bone, especially the talus, leading to collapse.
- Foot deformity. Flat or high-arched feet place abnormal stresses on the joint.
What are the symptoms?
- Pain, aching or sharp, worse with walking, standing and slopes, and often worst when you first stand up after sitting
- Stiffness, especially in the morning, with less ability to point or lift the foot
- Swelling that worsens with activity or at the end of the day
- Instability, a feeling the ankle may give way, especially on uneven ground
- Grinding, clicking or catching in the joint
- Deformity in advanced cases, where the ankle looks crooked
Symptoms often start only with high-impact activity and gradually affect everyday tasks.
Treatment without surgery
- Pain relief with paracetamol or anti-inflammatory medicines
- Footwear. Supportive or rocker-soled shoes
- Insoles or ankle braces to reduce joint loading
- Physiotherapy to maintain strength and movement
- Steroid injection for temporary relief of pain and inflammation
Surgery
- Arthroscopic debridement. Keyhole surgery to clean the joint in early arthritis, often including removal of bone spurs from the front of the ankle (cheilectomy).
- Osteotomy. Realigning the bones to offload the worn area, either above the ankle (supramalleolar osteotomy) or through the heel bone.
- Ankle distraction arthroplasty. A frame (external fixator) gently separates the joint surfaces for a period, encouraging repair tissue to form.
- Ankle fusion (arthrodesis). Fusing the bones to remove painful movement, often through a mini (small-incision) approach.
- Total ankle replacement. Replacing the joint surfaces with an implant to keep movement.
Ankle fusion or ankle replacement?
| Ankle fusion | Ankle replacement | |
|---|---|---|
| Pain relief | Excellent; removes painful movement | Excellent, if the implant is well aligned |
| Movement | No ankle movement, but the midfoot keeps some movement | Keeps ankle movement and a more natural walk |
| Function | High satisfaction on flat ground; slopes are harder | Better on uneven ground and slopes |
| Other joints | Extra stress on nearby joints; symptomatic arthritis in about 25% at 10 years, but no increase in further fusions at 25 years | In theory less stress on nearby joints; no difference in further fusions at 25 years |
| Durability | Permanent once fused | Wears out in time; 10 to 20% revised by 10 years |
| Further surgery | 10 to 15% may need metalwork removal and 5 to 10% revision. Over 25 years, 30% had another procedure, mostly minor | 20 to 25% may need minor or major revision at 5 to 10 years. Over 25 years, 35% had another procedure, typically more serious |
| Revision | Easier | Much more complex |
| Best for | Young, very active patients, poor bone quality or large deformity | Good bone and alignment, and a wish to keep movement |
Images from Prof Mason's practice
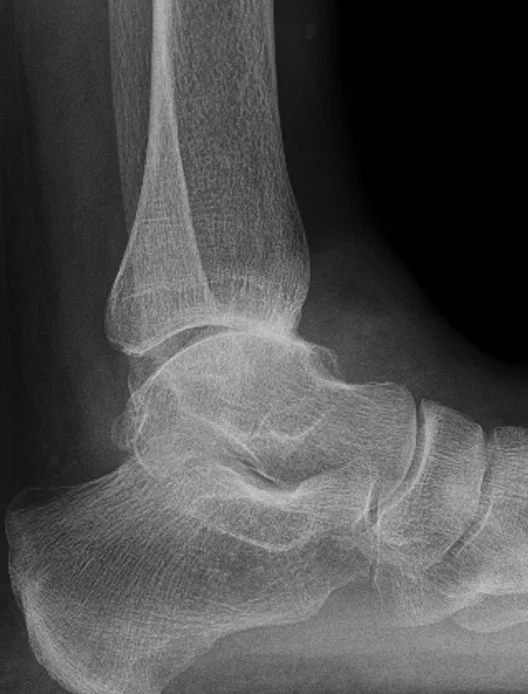
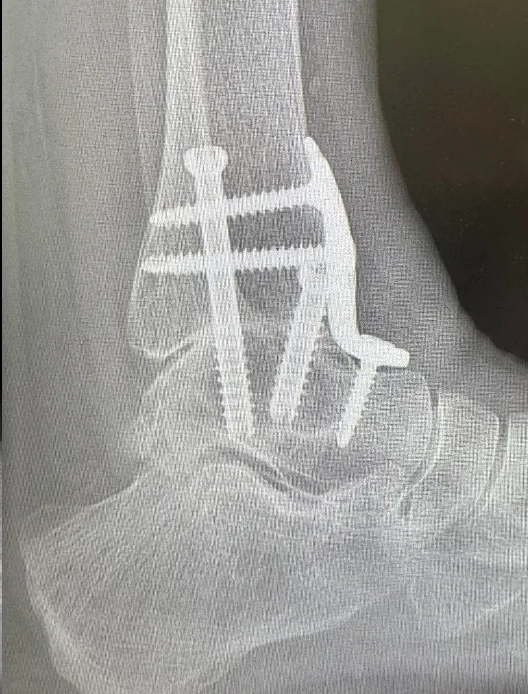
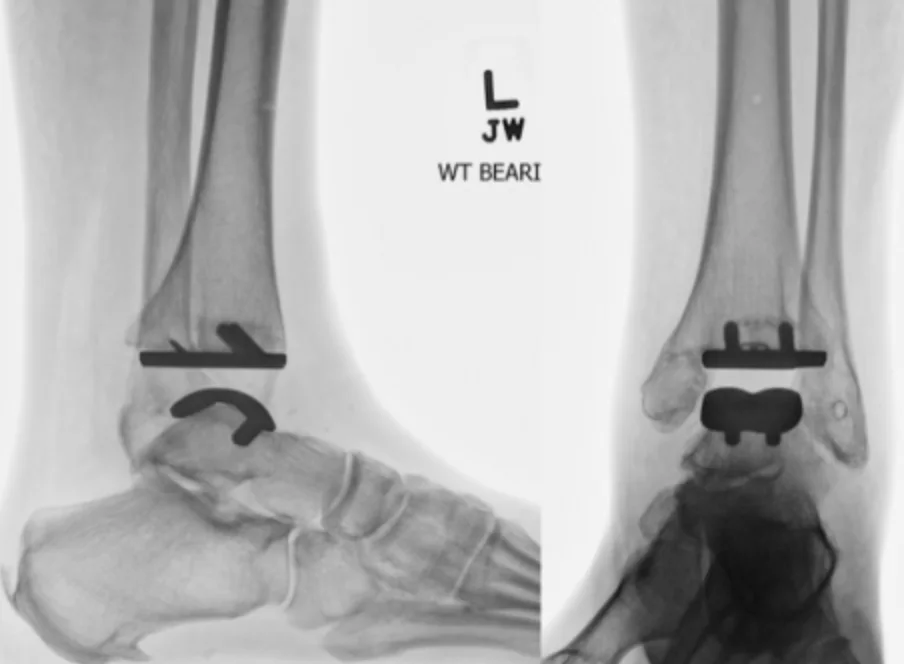
X-rays shown with patient identifiers removed. Results vary between patients.
Common questions
Will I be able to move my ankle after an ankle fusion?
The main ankle joint (the tibiotalar joint) will no longer bend up and down. The rest of the foot still moves: the joints below the ankle allow side-to-side movement for uneven ground, and the midfoot and forefoot let you push off when walking. Most people return to walking, cycling and driving, and some run short distances, though high-impact sport is limited.
Is return to sport different after fusion or replacement?
Very little. A study comparing the two (International Orthopaedics, 2012) found 76% of patients in both groups were still active in sport and recreation after surgery, with identical functional scores. Activity levels dropped slightly after either operation, but not differently between them.
How long does an ankle replacement last?
Modern implants often last 10 to 15 years or more, but they do wear out. Revision rates at 10 years are estimated at 10 to 20%, and revising a replacement is more complex than revising a fusion.
Talk it through with a specialist
Consultations at Spire Liverpool, Salford and the Isle of Man. New patients £250.

Consultant Foot and Ankle Surgeon, MB BCh, PhD, FRCS (Tr&Orth), FRCS (Glasg), SFHEA, FFSTEd. GMC 6074953. Hunterian Professor, Royal College of Surgeons of England.
Page last reviewed 25 October 2026. This information is general and does not replace an assessment.
Prof Mason's published research on this topic
Peer-reviewed papers by Prof Mason and his colleagues. Links open the paper or its PubMed record.
- Feroz J, Makwana N, Mason L, Halliwell P, Rushton A. Accuracy and quality of the British Orthopaedic Foot and Ankle Society (BOFAS) Registry: ankle arthrodesis. Foot and Ankle Surgery, 2021.
- Mason LW, Wyatt J, Weishman H, Butcher C, Molloy AP. Single-photon emission computed tomography in painful total ankle replacements. Foot & Ankle International, 2015.
- Fischer B, Mason LW. Reconstruction of severe ankle and pilon fracture malunions. Foot and Ankle Clinics, 2020.