
In short
Midfoot arthritis is wear of the joints in the middle of the foot, mainly the tarsometatarsal joints that link the forefoot to the arch. It causes aching across the top of the foot, swelling and sometimes a bony lump or a flattening arch. Stiff-soled shoes, insoles and image-guided steroid injections help many people. For severe arthritis, midfoot fusion is the most reliable treatment.
What is midfoot arthritis?
The midfoot contains several small joints, including the tarsometatarsal (TMT or Lisfranc) joints, which connect the forefoot to the hindfoot. They hold the arch stable and transfer weight as you walk. In arthritis, the cartilage of these joints wears away.
What causes it?
- Osteoarthritis, the most common cause, from wear over time
- Previous injury, especially a Lisfranc (midfoot) fracture or sprain, which can lead to arthritis years later
- Inflammatory arthritis, such as rheumatoid arthritis
- Foot shape, such as a flat or high-arched foot, which overloads the midfoot joints
What are the symptoms?
- Aching in the middle of the foot, worse when walking or standing
- Swelling over the top of the foot
- Stiffness
- A bony lump on top of the midfoot that rubs on shoes or laces
- A gradually collapsing arch
- Pain on uneven ground
Treatment without surgery
- Stiff-soled shoes reduce movement through the midfoot. Lacing that avoids pressure over the lump helps.
- Insoles support the arch and stiffen the shoe.
- Pain relief with paracetamol or anti-inflammatory medicines.
- Physiotherapy to keep the surrounding joints moving and strengthen supporting muscles.
- Activity changes to reduce long periods of standing or high impact.
Steroid injection
An image-guided steroid injection into the affected joint can reduce inflammation and pain. It also helps confirm which joint is the source of pain before any surgery. See the questions below for how well it works.
Surgery
- Midfoot fusion (arthrodesis). The gold standard for severe arthritis. The worn cartilage is removed and the bones are held with plates, screws or staples so they heal together. Through an incision on top of the foot, the affected joints are prepared, and occasionally bone graft is used to help healing.
- Removing bone spurs (cheilectomy) where a lump on top of the foot is the main problem.
- Nerve ablation. Interrupting the small nerve supplying the joint. Results are variable, so it is used selectively.
Images from Prof Mason's practice
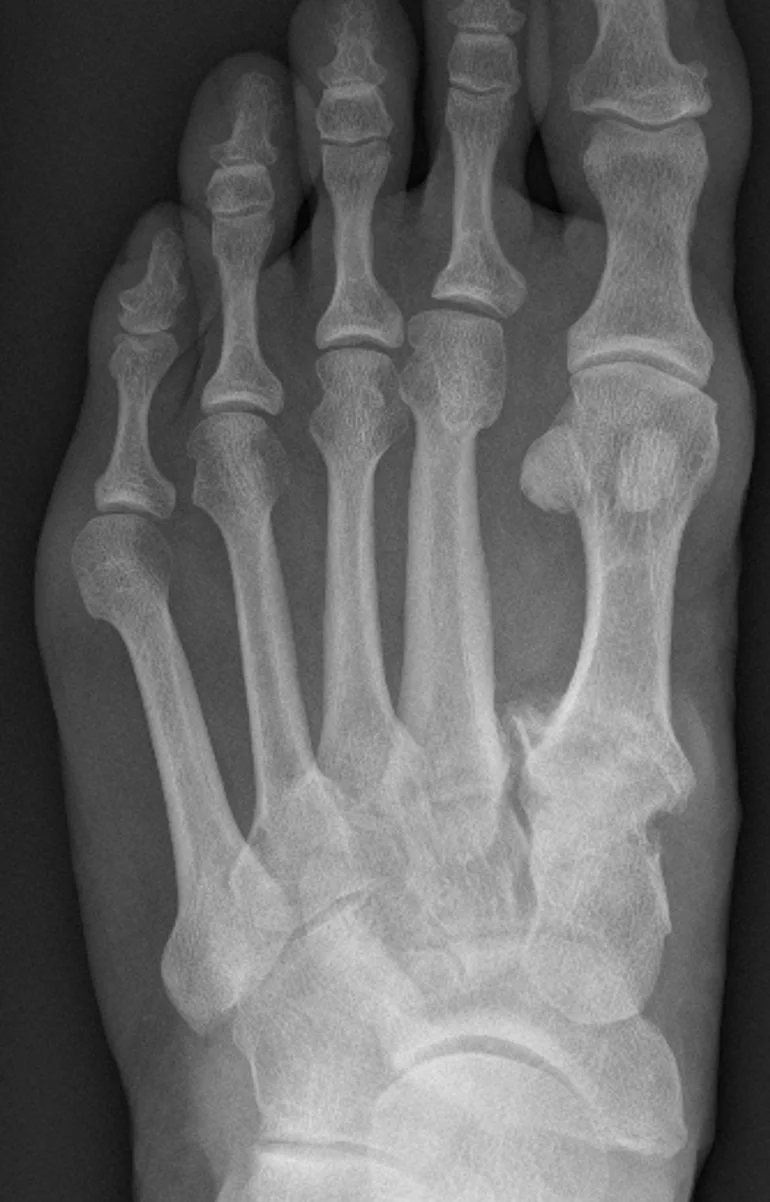
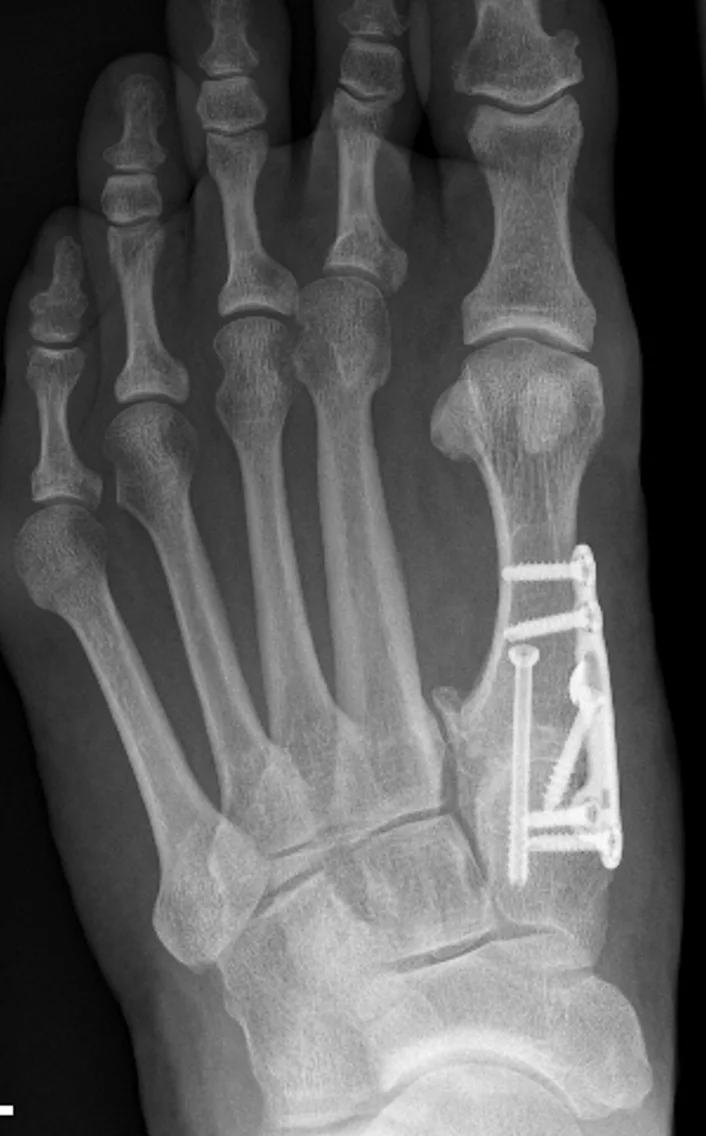
X-rays shown with patient identifiers removed. Results vary between patients.
Common questions
How well do steroid injections work for midfoot arthritis?
Most patients get moderate to good short-term relief, usually starting within a few days to a week. Relief typically lasts weeks to several months and often fades after three to six months. Injections work best for mild to moderate arthritis, and accuracy matters, so they are given under X-ray or ultrasound guidance. Repeated injections are generally limited because of possible effects on the surrounding tissues.
What is the usual recovery after midfoot fusion?
Weeks 1 to 6: no weight on the foot, in a cast or splint, with the foot raised. Weeks 6 to 12: gradually increasing weight in a boot as healing allows. Months 3 to 6: walking without crutches, physiotherapy, and managing swelling. Months 6 to 12: strengthening and return to normal activities, with full recovery expected by about a year.
What are the risks of midfoot fusion?
The main specific risk is non-union, where the bones do not fuse and further surgery may be needed. Smoking greatly increases this risk. Other risks include infection, nerve irritation and persistent swelling for many months. The fused joints no longer move, but because these joints only move a little normally, most people do not notice a functional difference.
Talk it through with a specialist
Consultations at Spire Liverpool, Salford and the Isle of Man. New patients £250.

Consultant Foot and Ankle Surgeon, MB BCh, PhD, FRCS (Tr&Orth), FRCS (Glasg), SFHEA, FFSTEd. GMC 6074953. Hunterian Professor, Royal College of Surgeons of England.
Page last reviewed 25 October 2026. This information is general and does not replace an assessment.
Prof Mason's published research on this topic
Peer-reviewed papers by Prof Mason and his colleagues. Links open the paper or its PubMed record.
- Ankers T, Singh A, Mason L, Sirikonda S. Arthrodesis of the second and third tarsometatarsal joints: comparison of clinical results using combined or individual plating techniques. Journal of Foot and Ankle Surgery (Asia-Pacific), 2023.
- Mason LW, Tanaka H. The tarsometatarsal joint and its association with hallux valgus. Bone & Joint Research, 2012.