
In short
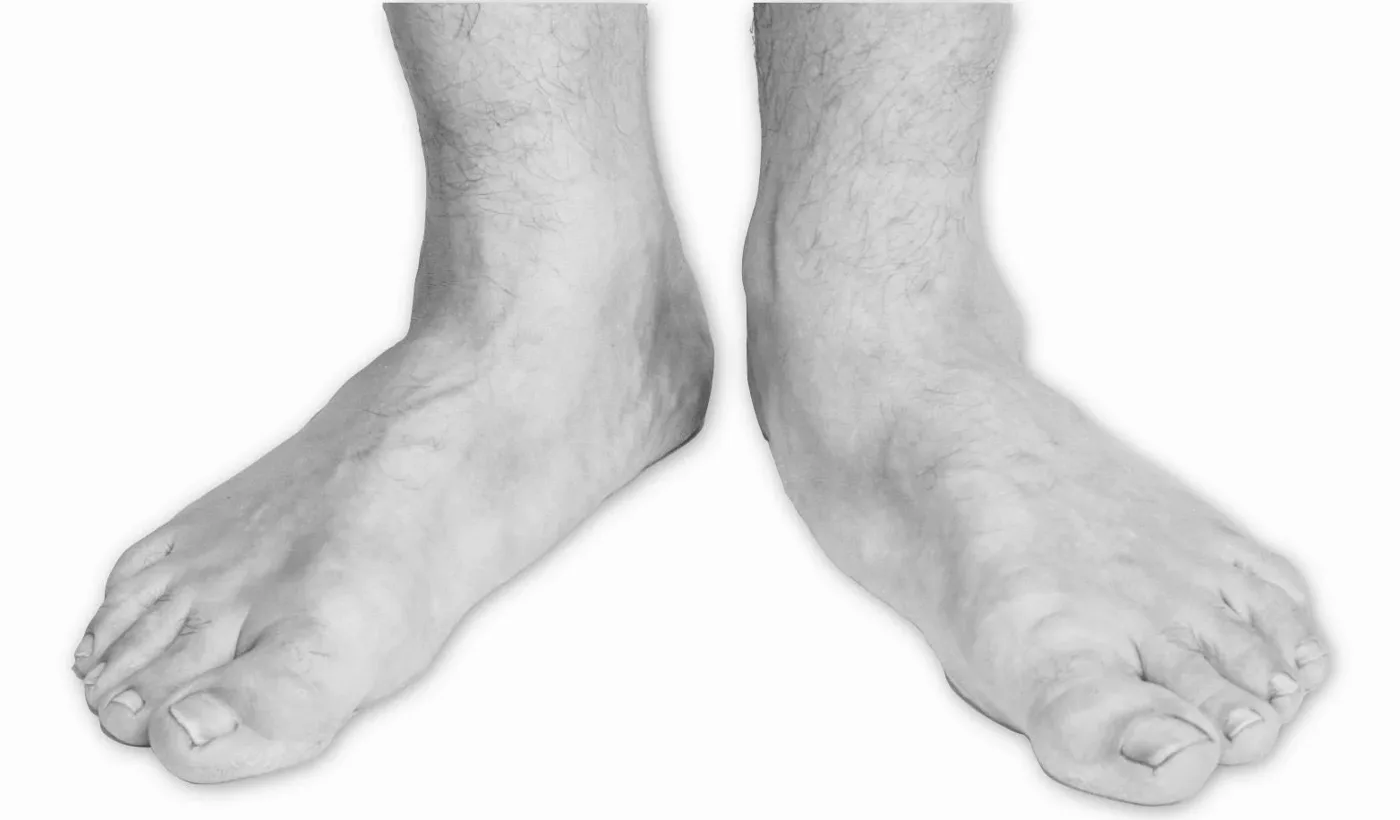
A flat foot (pes planus) is a low or collapsed arch. Many people with flat feet have no symptoms and need no treatment. When a flat foot develops in adulthood, the most common cause is weakening of the tibialis posterior tendon, which supports the arch. Insoles, supportive shoes and physiotherapy help most people. If the foot keeps collapsing or stays painful, reconstruction surgery can restore the arch.
What is a flat foot?
In a flat foot the inner arch is low, so most of the sole touches the ground when standing. It can be flexible, where the arch reappears when you sit or stand on tiptoe, or rigid, where the arch stays flat.
What causes it?
Present from childhood
- Inherited foot shape. Many people have always had flat feet.
- Flexible flat foot, the most common type in children and adults, often without symptoms.
- Tarsal coalition. An abnormal bridge between two foot bones, often noticed in adolescence, which makes the foot stiff.
Developing in adulthood
- Tibialis posterior tendon dysfunction (progressive collapsing foot deformity). The most common cause in adults. The tendon that supports the arch becomes weakened or damaged and the arch gradually collapses. The spring ligament under the arch is often stretched too.
- Injury to tendons, ligaments or bones of the foot.
- Arthritis, including rheumatoid arthritis.
- Loose ligaments (hypermobility).
- Body weight, which increases load on the arch.
- Nerve or muscle conditions that cause weakness, and diabetic neuropathy.
What are the symptoms?
- Pain along the inside of the foot and ankle, sometimes with swelling
- Aching arches and tired feet after standing or walking
- Pain on the outside of the ankle as the heel drifts outwards in advanced cases
- Difficulty standing on tiptoe on one leg
- Knee, hip or back discomfort from altered alignment
- Shoes wearing unevenly
Treatment without surgery
- Insoles (orthotics). Arch supports, from off-the-shelf to custom-made, to support and realign the foot.
- Supportive footwear with a firm heel counter. Avoid flip-flops and flat, unsupportive shoes.
- Physiotherapy. Strengthening the tibialis posterior and calf, and stretching a tight calf.
- Activity changes, such as cycling or swimming instead of running.
- Pain relief and weight management.
- A brace or boot for a period in active tibialis posterior tendon problems.
Flat foot surgery
Surgery is for flat feet that remain painful or keep collapsing despite these measures. It is tailored to the cause and usually combines several procedures:
- Calf lengthening (gastrocnemius release) to reduce the pull that flattens the foot
- Tendon repair or transfer to replace a failing tibialis posterior tendon
- Spring ligament reconstruction to support the arch from below
- Osteotomy. Realigning bones, commonly moving the heel bone inwards, lengthening the outer foot or bringing the big toe side of the foot down
- Fusion of hindfoot joints when there is arthritis or a rigid deformity
- Subtalar arthroereisis, an implant to limit excessive rolling in, in selected cases
Images from Prof Mason's practice
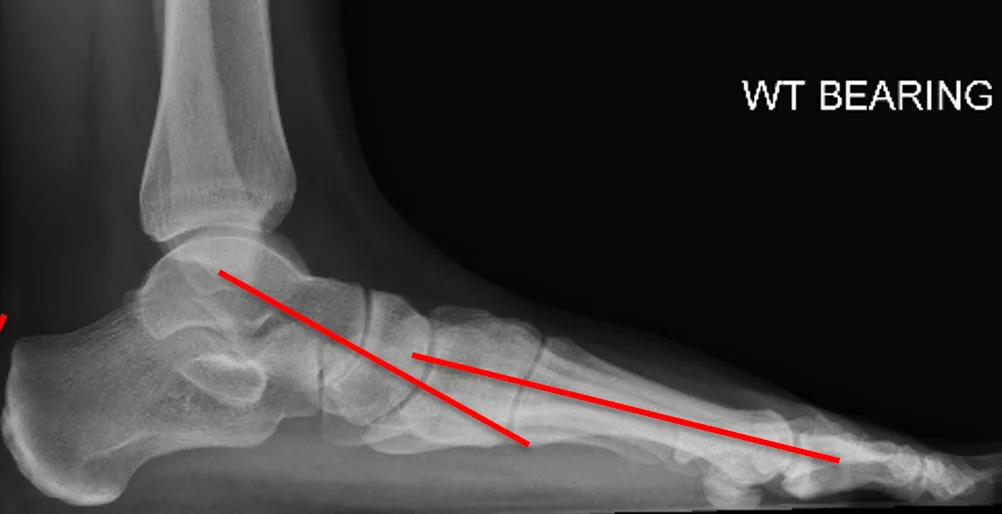
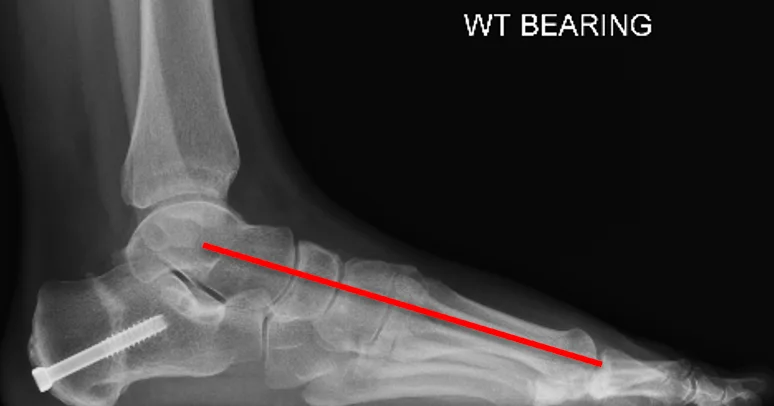
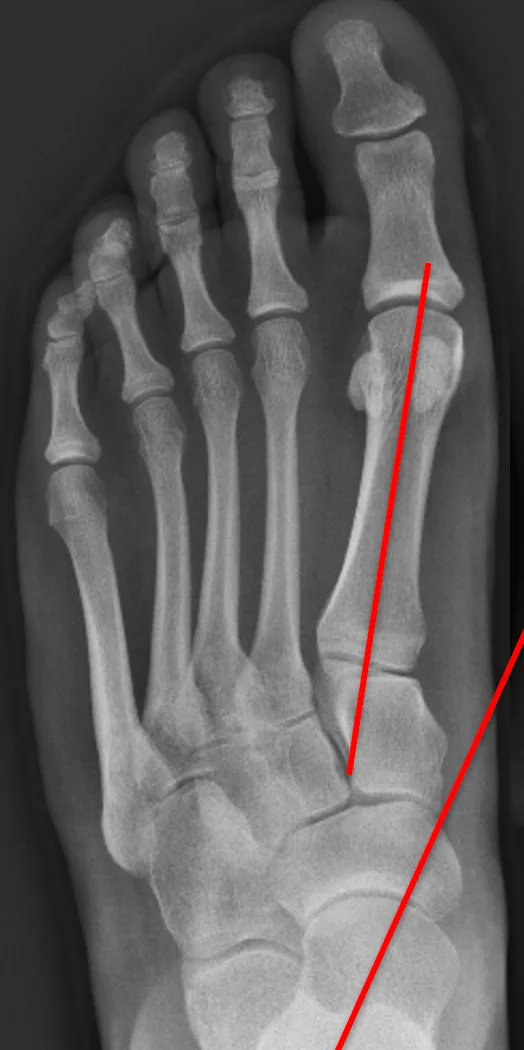
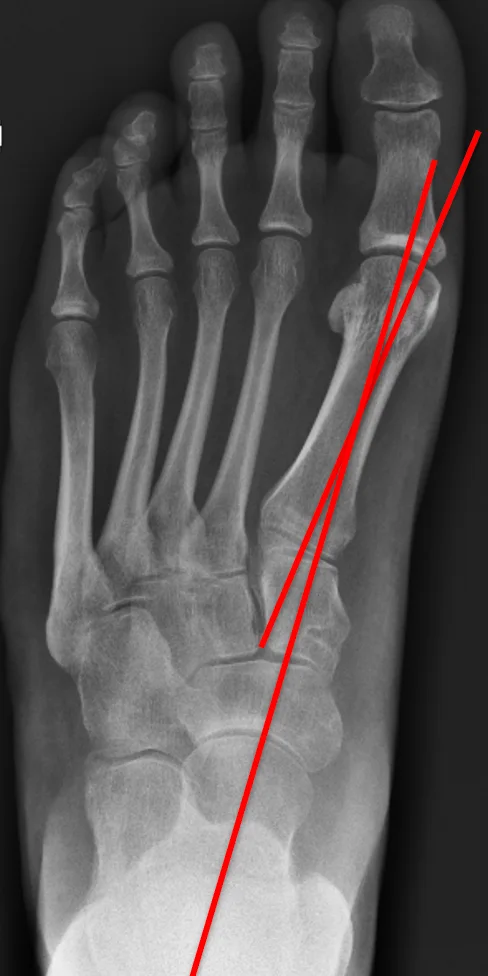
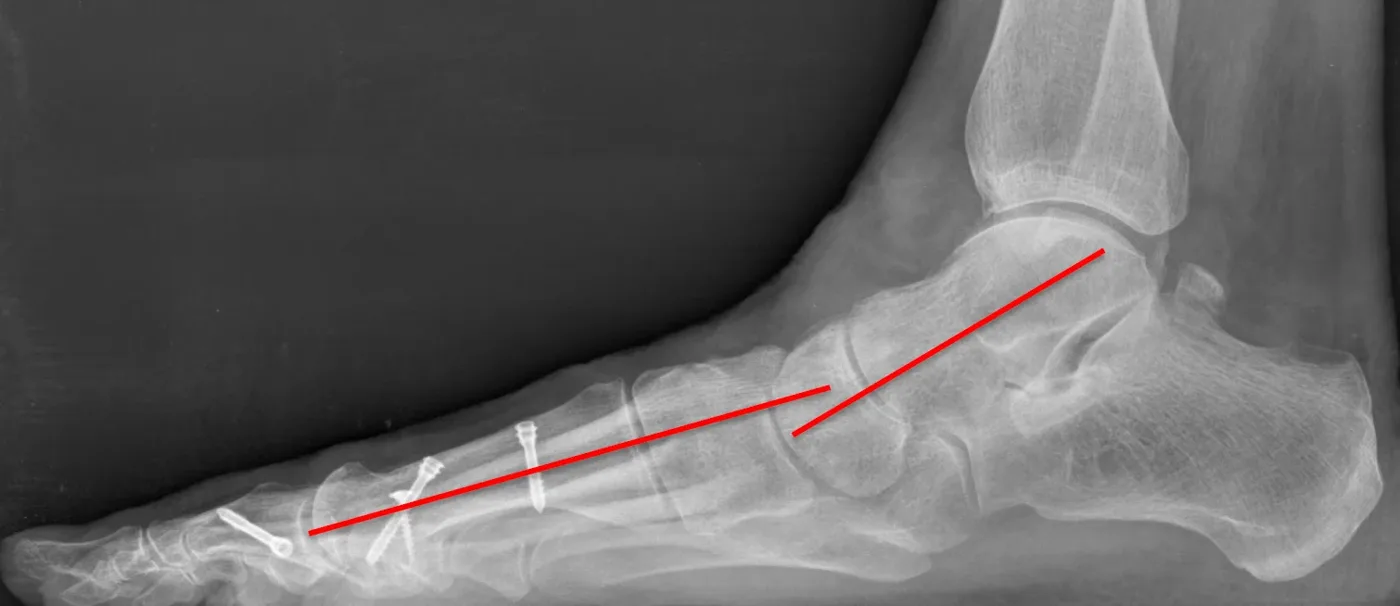
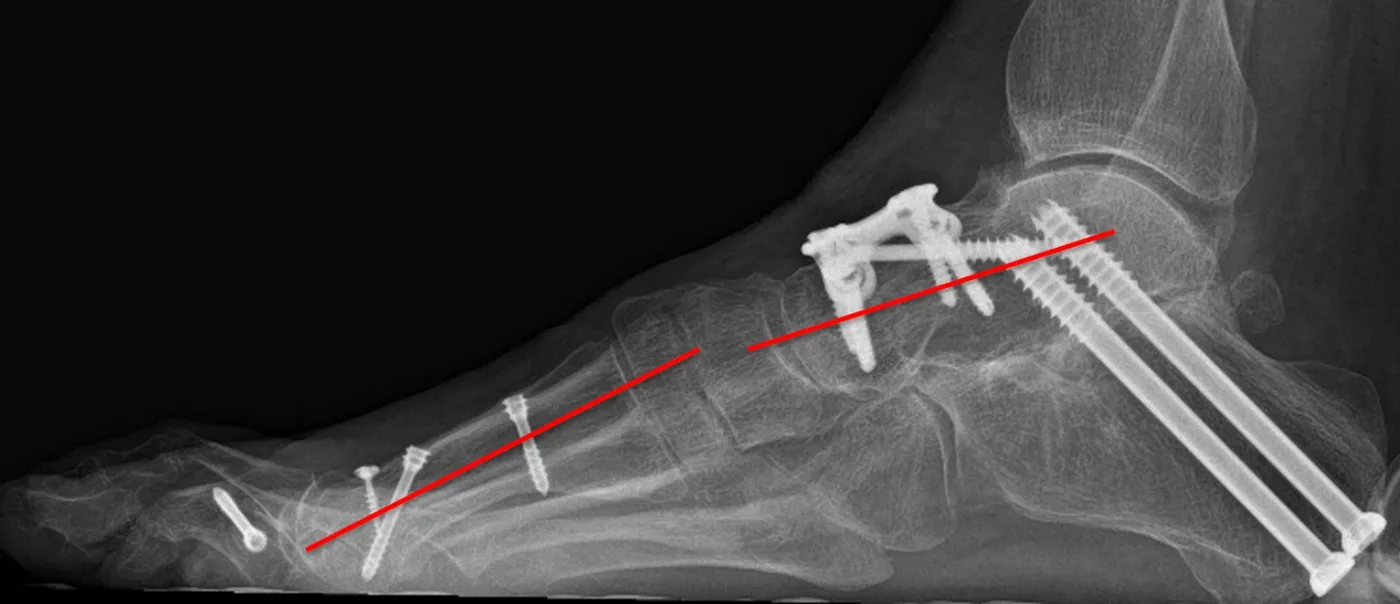
X-rays shown with patient identifiers removed. Results vary between patients.
Common questions
What is the usual recovery after flat foot reconstruction?
First 6 to 8 weeks: no weight on the foot, in a cast or boot. Months 2 to 3: partial weight-bearing and physiotherapy. Months 3 to 6: full weight-bearing and a gradual return to normal activities. Months 6 to 12: continued improvement, with some residual stiffness or mild discomfort in some people.
What affects recovery?
The type of surgery (tendon and ligament repairs recover faster than bone realignment or fusion), your age and general health, conditions such as diabetes, smoking, and how closely you follow the rehabilitation plan.
Do flat feet in children need treatment?
Usually not. Most children have flexible flat feet and the arch develops as they grow. A flat foot that is stiff, painful or affects only one side should be assessed.
Talk it through with a specialist
Consultations at Spire Liverpool, Salford and the Isle of Man. New patients £250.

Consultant Foot and Ankle Surgeon, MB BCh, PhD, FRCS (Tr&Orth), FRCS (Glasg), SFHEA, FFSTEd. GMC 6074953. Hunterian Professor, Royal College of Surgeons of England.
Page last reviewed 25 October 2026. This information is general and does not replace an assessment.
Prof Mason's published research on this topic
Peer-reviewed papers by Prof Mason and his colleagues. Links open the paper or its PubMed record.
- Heyes G, Swanton E, Vosoughi AR, Mason LW, Molloy AP. Comparative study of spring ligament reconstructions using either hamstring allograft or synthetic ligament augmentation. Foot & Ankle International, 2020.
- Swanton E, Fisher L, Fisher A, Molloy A, Mason LW. An anatomic study of the naviculocuneiform ligament and its possible role maintaining the medial longitudinal arch. Foot & Ankle International, 2019.
- Chapman J, Dalal N, Molloy A, Jenkinson H, Singh A, Sirikonda S, Mason L. Association of fusion of the first metatarsophalangeal joint and pes planus deformity correction. Foot & Ankle International, 2023.
- Heyes G, Vosoughi AR, Weigelt L, Mason LW, Molloy AP. Pes planus deformity and its association with hallux valgus recurrence following Scarf osteotomy. Foot & Ankle International, 2020.