
In short
Big toe arthritis, or hallux rigidus, is wear of the cartilage in the joint at the base of the big toe. It causes pain, stiffness and often a bony lump on top of the joint. Stiff-soled or rocker shoes, insoles and injections help many people. If pain continues, a cheilectomy (removing the bone spurs) suits early arthritis, and a big toe fusion is the most reliable treatment for severe arthritis.
What is big toe arthritis?
Hallux rigidus is arthritis of the first metatarsophalangeal (MTP) joint, the joint where the big toe meets the foot. The cartilage wears away, the joint becomes painful and stiff, and bone spurs often form on top. Because you push off from this joint with every step, it can make walking uncomfortable.
What causes it?
- Wear and tear over time, the most common cause
- Previous injury such as a fracture or a “stubbed” or sprained big toe (turf toe)
- Foot shape, including a flat foot, high arch or bunion
- Inflammatory conditions such as rheumatoid arthritis or gout
What are the symptoms?
- Pain in the big toe joint, especially when walking or pushing off
- Stiffness, particularly when bending the toe upwards
- Swelling around the joint
- A bony lump on top of the joint, sometimes called a dorsal bunion
- Walking on the outside of the foot to avoid the painful joint
Treatment without surgery
- Footwear. Stiff-soled shoes stop the joint bending. Rocker-bottom soles let the foot roll through the step without bending the toe. A deep, wide toe box avoids pressure on the lump.
- Insoles. Insoles with a stiffened forefoot reduce movement at the joint.
- Pain relief. Paracetamol or anti-inflammatory medicines.
- Activity changes. Reducing activities that force the toe upwards.
- Steroid injection. Can reduce pain for a period, especially in milder arthritis.
Surgery for big toe arthritis
- Cheilectomy. The bone spurs and the top part of the joint are removed so the toe can bend further without catching. It works best when the arthritis is mainly on the top of the joint.
- Fusion (arthrodesis). The worn joint surfaces are removed and the bones are held together with a plate and screws so they heal as one. The toe no longer bends at that joint, but pain relief is excellent and long-lasting. It is the gold standard for severe arthritis.
- Osteotomy. Cutting and realigning the bone to offload the joint, used in selected cases.
- Joint replacement. Available, but with less predictable results, so used less often.
Recovery after big toe fusion
Most patients walk in a protective post-operative shoe or boot for about six weeks while the bones fuse. Swelling continues to settle over several months, and most people are back to normal activity by three to six months.
Images from Prof Mason's practice
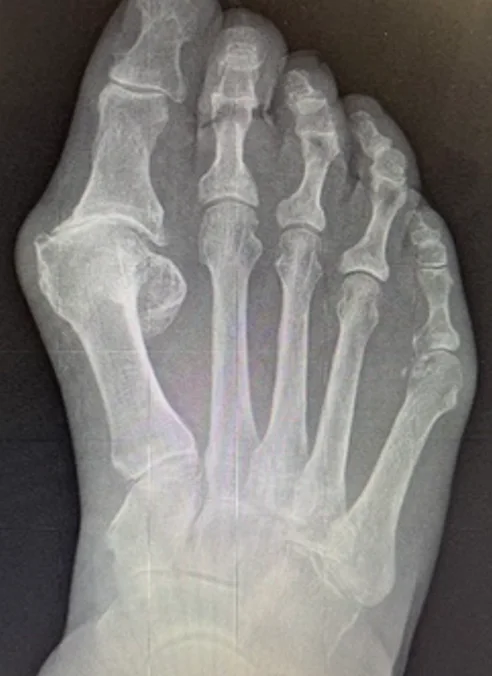
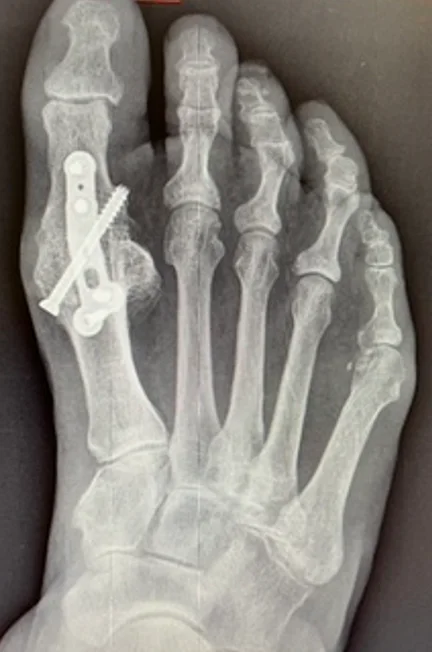
X-rays shown with patient identifiers removed. Results vary between patients.
Common questions
Can you have a big toe fusion if you are young?
Yes. Age alone does not rule out a fusion. The decision depends on how severe the arthritis is, how much it limits you and whether other treatments have worked. Younger, active people may try a joint-preserving option such as a cheilectomy first. Long-term studies have found that fusion works as well in people under 50 as in older patients.
Can I wear heels after a big toe fusion?
Many people can, within limits. The toe is fused at a slight upward angle, so low heels of around 1 to 2 inches are usually manageable, and some people wear higher heels for shorter periods. In one study, most patients who wore heels before surgery continued to do so afterwards, generally at the same height. Very high heels are usually uncomfortable.
Can I still play sport after a fusion?
Most people return to their sport. Studies of several hundred patients show the large majority find walking, golf, cycling, gym work, hiking and tennis the same or easier after fusion, with only a small minority finding it harder. Return to sport is typically around three months after surgery. High-impact sports with lots of pushing off from the toes can be more challenging.
Is a big toe joint replacement an option?
Big toe replacements exist but their results are less consistent than fusion, so they are used less often. Prof Mason will discuss whether any joint-preserving option is reasonable for you.
Talk it through with a specialist
Consultations at Spire Liverpool, Salford and the Isle of Man. New patients £250.

Consultant Foot and Ankle Surgeon, MB BCh, PhD, FRCS (Tr&Orth), FRCS (Glasg), SFHEA, FFSTEd. GMC 6074953. Hunterian Professor, Royal College of Surgeons of England.
Page last reviewed 25 October 2026. This information is general and does not replace an assessment.
Prof Mason's published research on this topic
Peer-reviewed papers by Prof Mason and his colleagues. Links open the paper or its PubMed record.
- Jadhakhan F, Makwana N, Mason L, Halliwell P, Rushton A. Clinical outcomes of first metatarsophalangeal joint arthrodesis using the BOFAS Registry: a prospective cohort study. Journal of Foot and Ankle Research, 2025.
- Weigelt L, Redfern J, Heyes G, Butcher C, Molloy A, Mason L. Risk factors for non-union after first metatarsophalangeal joint arthrodesis with a dorsal locking plate and compression screw construct: correction of hallux valgus is key. Journal of Foot and Ankle Surgery, 2021.
- Chapman J, Dalal N, Molloy A, Jenkinson H, Singh A, Sirikonda S, Mason L. Association of fusion of the first metatarsophalangeal joint and pes planus deformity correction. Foot & Ankle International, 2023.