
In short
A bunion (hallux valgus) is a bony bump at the base of the big toe, caused by the first metatarsal drifting outwards while the big toe angles in towards the other toes. Wider shoes, padding and insoles often ease the pain. If it keeps hurting, surgery realigns the bone, either through small keyhole incisions (MIS), a Scarf osteotomy or, for arthritic or severe bunions, a fusion.
What is a bunion?
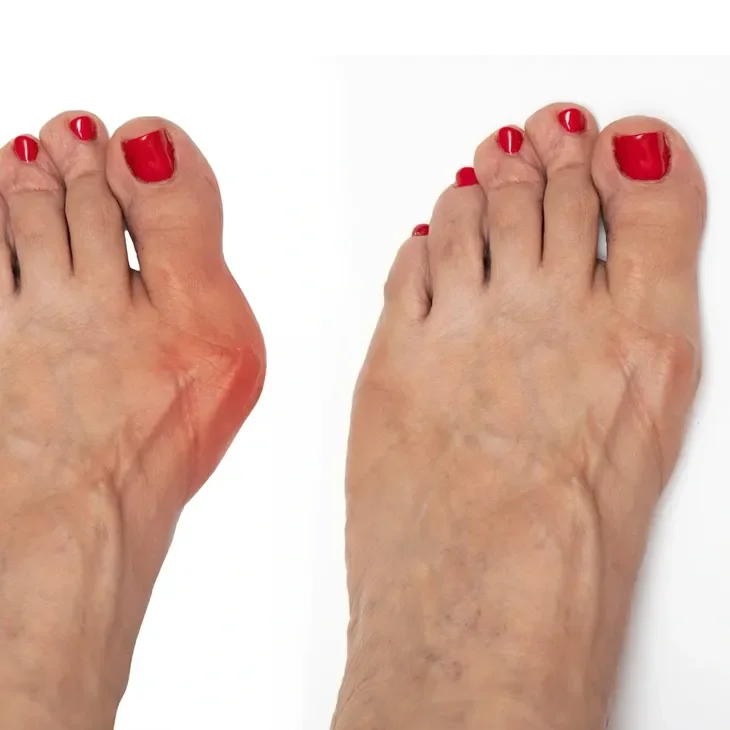
A bunion, or hallux valgus, is a bony prominence on the inner side of the foot at the base of the big toe. The first metatarsal bone drifts outwards and the big toe angles in towards the smaller toes. The bump rubs on shoes, and the joint can become swollen and painful.
What causes bunions?
The exact cause is not fully understood. Bunions usually come from a mix of factors:
- Genetics and foot shape. Bunions often run in families.
- Foot mechanics. A flat or flexible foot and the shape of the joint at the base of the first metatarsal both play a part.
- Footwear. Tight, pointed or high-heeled shoes do not usually cause a bunion on their own, but they make it more painful and can speed it up.
What are the symptoms?
- A bump at the base of the big toe that rubs in shoes
- Pain, redness or swelling over the joint
- The big toe pushing against or crossing the second toe
- Hard skin under the ball of the foot or on the smaller toes
- Difficulty finding shoes that fit
Treatment without surgery
Non-surgical treatment does not straighten the toe, but it often controls the symptoms well:
- Footwear. Shoes with a wide, deep toe box take pressure off the bump.
- Padding and insoles. Bunion pads, toe spacers and insoles can redistribute pressure, especially if the arch is flattening.
- Pain relief. Paracetamol or anti-inflammatory medicines can help flare-ups.
- Exercises. Stretching and strengthening the foot and calf can ease discomfort.
Bunion surgery
Surgery is considered when pain persists despite these measures. The operation is chosen to suit your foot.
Osteotomy (bone realignment), including the Scarf osteotomy
The first metatarsal is cut and moved back into position, then held with small screws. This keeps the joint moving and corrects the angle of the bone in three dimensions. It is the most common bunion operation.
Minimally invasive (keyhole) bunion surgery
The same principle, realigning the bone, is carried out through several very small incisions using specialised instruments and X-ray guidance. It may reduce soft tissue damage and scarring.
Fusion (arthrodesis)
For bunions with arthritis in the big toe joint, very severe deformity or recurrence after previous surgery, the joint can be fused. This gives reliable pain relief and a very low chance of the bunion returning, at the cost of movement at that joint. Fusion of the joint further back in the foot (the first tarsometatarsal joint) is sometimes used for a very mobile foot.
What are the risks of surgery?
All surgery carries risks, including infection, stiffness, numbness around the scar, delayed bone healing, and recurrence of the bunion. Prof Mason will go through the risks that apply to your operation at your consultation, and written consent information is available on the surgery details page.
Images from Prof Mason's practice
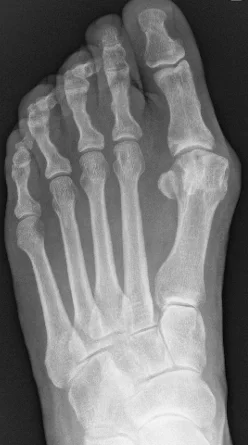
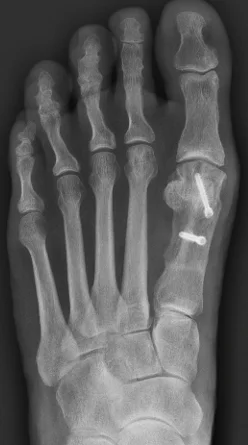
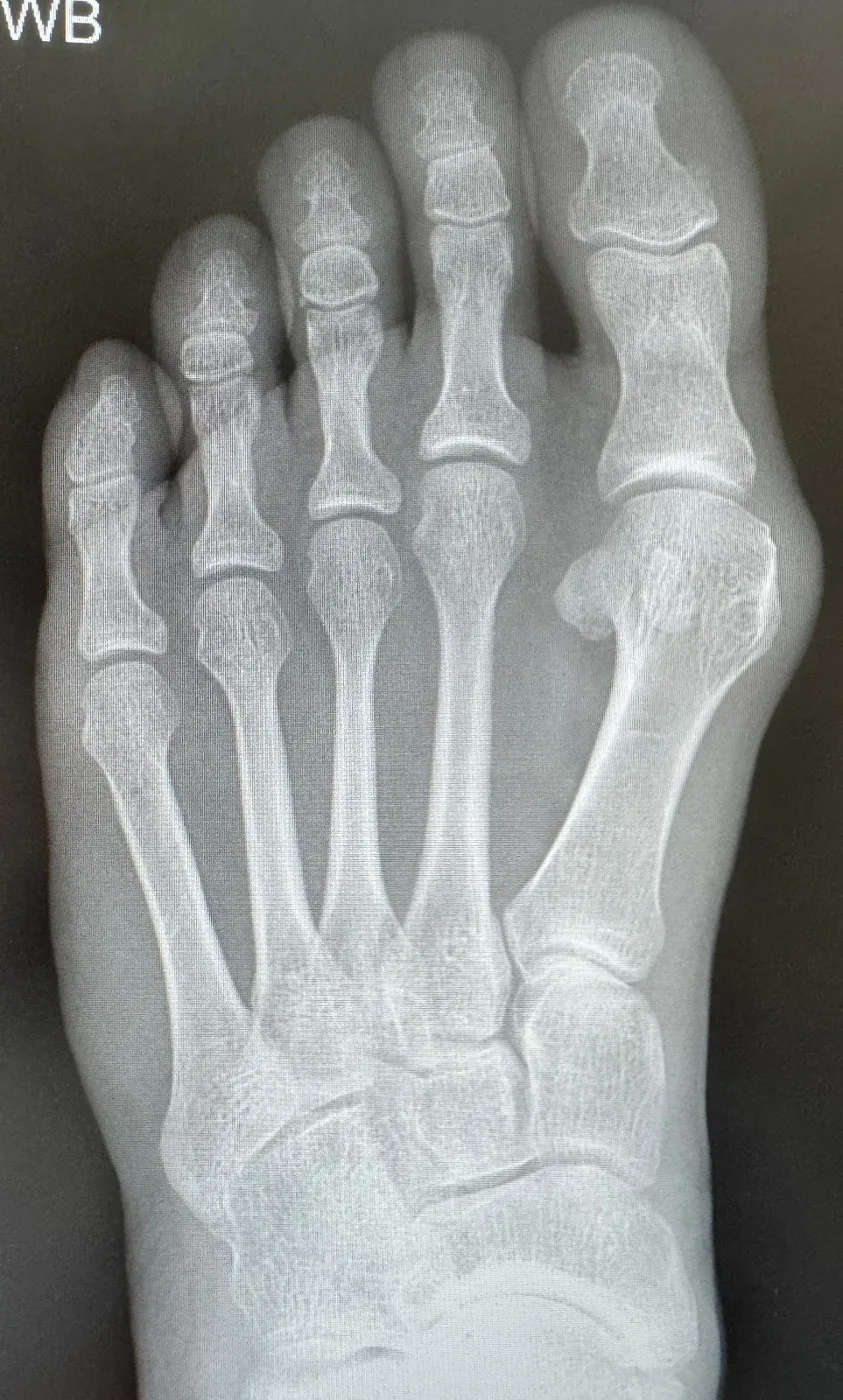
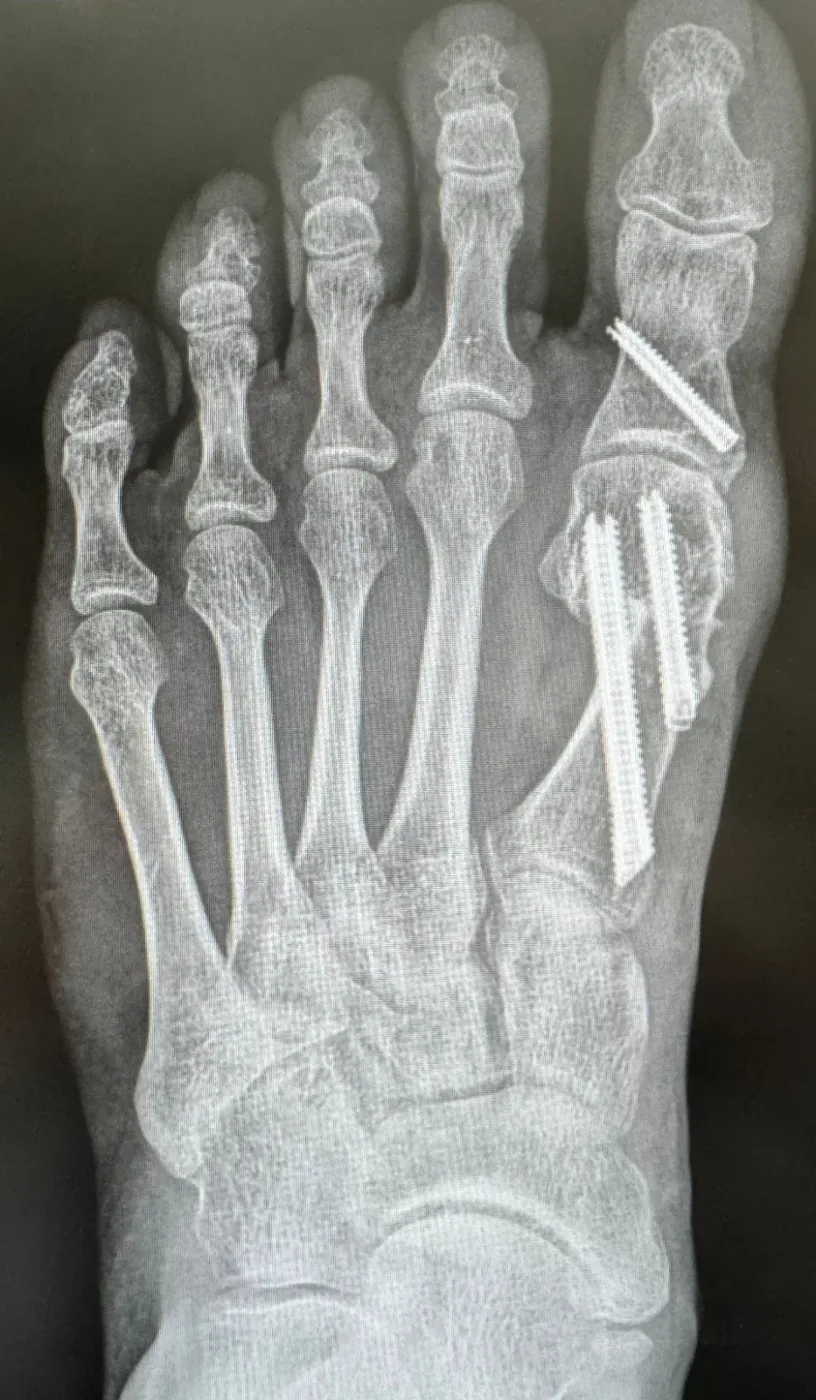
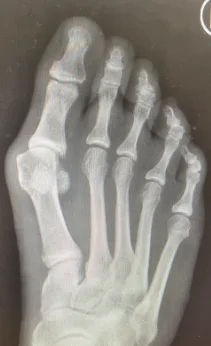
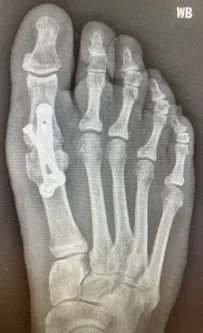
X-rays shown with patient identifiers removed. Results vary between patients.
Common questions
What happens if I leave my bunion untreated?
Some bunions never cause trouble and do not need treatment. Others slowly get worse, which can mean more pain in shoes, a change in how you walk, stiffness, arthritis in the big toe joint, corns and calluses, and in a small number of people skin breakdown over the bump. Treatment is worth considering when the bunion is limiting what you do.
Is keyhole (MIS) bunion surgery better than open surgery?
Keyhole surgery uses several tiny incisions and X-ray guidance instead of one longer cut. It may mean smaller scars, less swelling and an easier early recovery, and the correction it achieves is comparable to open surgery. It is not right for every foot. Prof Mason has used minimally invasive techniques for around ten years and will advise which approach suits your bunion.
How long is recovery after bunion surgery?
Most people walk in a special post-operative shoe from the day of surgery, usually for about six weeks, then move into wide, comfortable shoes. Swelling settles gradually over three to six months. Driving and return to work depend on which foot is operated on and the type of job. You will be given a recovery plan specific to your operation.
Will my bunion come back?
Recurrence is possible after any bunion operation. Our research has shown that a flat foot is linked with a higher chance of recurrence after Scarf osteotomy, which is one reason the whole foot is assessed, not just the big toe. For bunions with a high risk of recurrence, a fusion may be recommended.
Talk it through with a specialist
Consultations at Spire Liverpool, Salford and the Isle of Man. New patients £250.

Consultant Foot and Ankle Surgeon, MB BCh, PhD, FRCS (Tr&Orth), FRCS (Glasg), SFHEA, FFSTEd. GMC 6074953. Hunterian Professor, Royal College of Surgeons of England.
Page last reviewed 25 October 2026. This information is general and does not replace an assessment.
Prof Mason's published research on this topic
Peer-reviewed papers by Prof Mason and his colleagues. Links open the paper or its PubMed record.
- Lewis T, Malhotra K, Makwana N, Wood E, Humphrey J, Mason L. Lifetime cost-effectiveness of hallux valgus correction surgery using patient-reported outcomes from the National British Orthopaedic Foot and Ankle Registry in the United Kingdom. The Foot, 2026.
- Marusza CJ, Stringer H, Redfern J, Sangoi D, Welck M, Mason LW, Malhotra K. The position, orientation and morphology of the peroneus longus tubercle in hallux valgus: a weight-bearing CT assessment. The Foot, 2025.
- Weigelt L, Heyes G, Mason L, Molloy A. The Scarf osteotomy. Techniques in Foot & Ankle Surgery, 2021.
- Heyes G, Vosoughi AR, Weigelt L, Mason LW, Molloy AP. Pes planus deformity and its association with hallux valgus recurrence following Scarf osteotomy. Foot & Ankle International, 2020.
- Swanton E, Mason LW, Molloy A. How do I use the Scarf osteotomy to rotate the metatarsal and correct the deformity in three dimensions?. Foot and Ankle Clinics, 2018.
- Nebhani N, Trivedy M, Heyes G, Molloy A, Mason L. Hallux valgus interphalangeus measurement: comparison of two radiographic methods. Foot & Ankle Specialist, 2024.
- Mason LW, Tanaka H. The tarsometatarsal joint and its association with hallux valgus. Bone & Joint Research, 2012.
- Perera A, Mason LW, Stephens MM. The pathogenesis of hallux valgus. Journal of Bone and Joint Surgery (American), 2011.